
Luljeta Abdullahu1*, Armend Jashari1, Naser Gjonbalaj2, Fisnik Kurshumliu3, Nimet Orqusha4, Brunilda Haxhiu5, Basri Lenjani6, Ilir Kurtishi5, Ylli Kaçiu1,2, Fitore Murati7 and Vjollca Dedushaj Fazliu8
1Nuclear Medicine Department - University Clinical Center of Kosovo, Republic of Kosovo
2Clinic of Radiology, University Clinical Center of Kosovo
3Institute of Pathology-University Clinical Center of Kosovo, Republic of Kosovo
4Professor, Assistant Dr. Faculty of Medicine, University of Prishtina “Hasan Prishtina”, Prishtina, Republic of Kosovo
5Oncology Clinic, University Clinical Center of Kosovo, Republic of Kosovo
6Emergency Clinic, University Clinical Centre of Kosovo, Republic of Kosovo
7Physiotherapeutic - University Clinical Center of Kosovo, Republic of Kosovo
8Internal Medicine - Endocrinologist Private Praxis "Vital Health Group" Agim Ramadani n.n. Republic of Kosovo
*Corresponding Author: Luljeta Abdullahu and Armend Jashari, Nuclear Medicine Department -University Clinical Center of Kosovo, Republic of Kosovo.
Received: July 18, 2024; Published: August 23, 2024
Citation: Luljeta Abdullahu and Armend Jashari., et al. “Solitary Bone Metastases of the Thoracic Spine at Th-11 from Uveal Malignant Melanoma: A Rare Entity and Literature Review - A Rare Case Report”. Acta Scientific Medical Sciences 8.9 (2024): 103-107.
The aim of this study is to present a rare case of a patient with uveal malignant melanoma who presented with solitary metastases to the thoracic vertebra three years after eye enucleating. Bone metastasis from retinal melanoma is extremely rare and is usually associated with involvement of organs primarily in the liver or lungs.
We report a rare case of a patient with malignant (ocular) melanoma who presented with a single (solitary) metastasis to the thoracic vertebra (Th-11) three years after enucleating, without involvement of other organs. Imaging studies included computed tomography (CT), MRI, whole-body bone scan with 99mTc-MDP, and confirmation via core biopsy.
Discussion: Early detection and a multidisciplinary approach are very important in the management of patients with bone metastases from malignant melanoma.
Conclusion: The involvement of specialists from different fields such as radiology, pathology, medical oncology, radiation oncology, and surgical oncology can lead to a better outcome for the patient. In our case radiation and operative surgery could benefit for patients with solitary bone metastasis to achieve long-term survival.
Keywords: Uvula Melanoma; CT Scan; MRI; Whole Body Bone Scan; 99mTc-MDP; Dual Head Gamma Camera Siemens; Biopsy
Malignant melanoma represents only 3% of all melanomas and its incidence is increasing worldwide [1,2]. It occurs in about five to seven individuals per million. Uveal melanoma (UM) arises from melanocytes located in the choroid layer between the sclera and the retina. Although it is the most common primary eye tumor, only about 2,500 cases are diagnosed per year in the United State [3]. Despite optimal treatment (surgical or radiation), metastases often develop within an average period of 24-48 months and are associated with poor survival. Bone metastases from malignant melanoma are less frequent than liver or brain metastases, ranging from 11% to 17% [4].
Metastasis of malignant melanoma of ciliary origin can spread from local extension, lymphatic vessels, or blood circulation, as in our case of retinal-uvula melanoma [4,5]. Distant melanoma spread through the bloodstream usually involves the lungs, gastrointestinal tract, brain, parotids, heart, and bones to a lesser extent.
Single (solitary) bone metastasis of malignant retinal melanoma is extremely rare and is usually associated with involvement of other organs [6]. Bone metastases from malignant melanoma are less common, ranging from 11% to 17%. The most common forms of metastatic melanoma of the spine are vertebral metastatic melanoma and intramedullary metastatic melanoma. One study reported 133 cases of vertebral metastatic melanoma over 11 years [7] and there have been nine reported cases of intramedullary spinal cord metastatic melanoma [8].
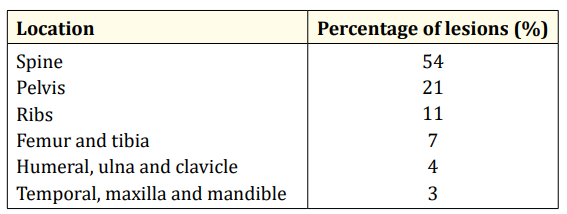
Table 1: Skeletal distribution of the lesions [10].
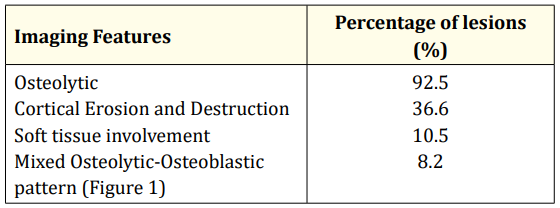
Table 2: Uploaded by [9].
A man in his fourth decade presented with a complaint of pain at the level of the thoracic ring of the Th11 thoracic vertebrae two weeks prior to a scheduled skeletal scintigraphy. He had previously been treated for retinal melanoma three years ago, which resulted in the enucleating of his right eye at another medical center. The histopathological examination after the enucleation revealed a malignant melanoma of the retina with a diameter of 2x1 cm. After the patient presented to our hospital three years after the initial diagnosis, various radiological examinations such as computed tomography (CT), magnetic resonance imaging (MRI), wholebody bone scan with 99mTc-MDP, and a CT-directed biopsy were performed. These tests, along with imaging results shown in Figures 1, 2, and 3, confirmed the diagnosis of metastatic malignant melanoma.
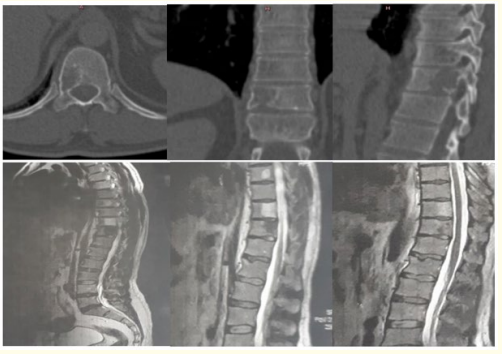
Figure 1: CT-scan and Sagittal MRI shows lytic change (bone destruction) on the right lateral pedicles arches of Th- 11.
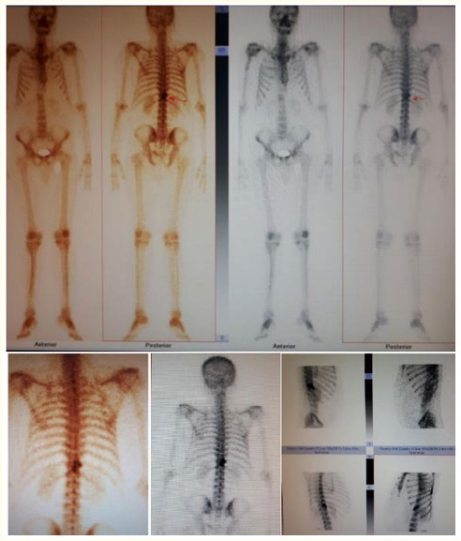
Figure 2: The bone scan showed a more intense accumulation of the tracer on the affected side of the vertebra, as well as an osteolytic defect in the right lateral part, indicative of an unusual mixed osteolytic-osteoblastic metastatic pattern located at the Th-11 thoracic vertebra. Additionally, static spots were observed in the anterior, posterior, lateral, and oblique projections, further confirming the presence of metastatic malignant melanoma in the affected vertebra.
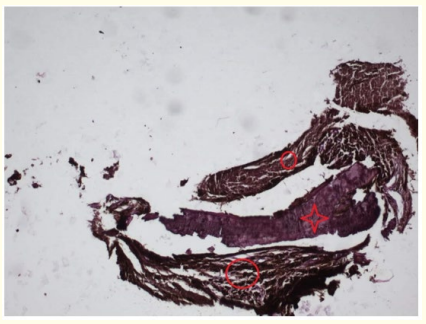
Figure 3: Histopathological outcome of Metastatic Malignant Melanoma (circle corresponds to tumor tissue, star corresponds to calcified bone trabeculae).
Bone metastases from uveal malignant melanoma are often found in the axial skeleton and are typically osteolytic. The main goals of treatment for metastatic bone damage are pain relief, prevention or treatment of pathological fractures and decompression of the spinal cord if necessary [10,11]. Skeletal metastases are usually associated with advanced stages of the disease and may occur simultaneously with the spread of the cancer to other organs [9].
Radiography and computed tomography (CT) are often the first imaging modalities used to assess skeletal metastatic disease. However, magnetic resonance imaging (MRI) can also be helpful in the diagnosis of spinal tumors, including spinal melanoma, by showing increased signal intensity in the vertebral body with soft tissue extension into the extradural space [7,12].
Bone scan is the standard method for assessment of skeletal metastatic disease, but FDG PET/CT has been shown to be as accurate as bone scan in identifying skeletal metastatic disease, and it offers the added advantage of being able to perform cancer staging of different organ systems in the same examination [13].
While there is no standard treatment for bone metastases from uveal melanoma, radical bone resection followed by radiotherapy with or without chemotherapy is currently the most effective treatment for selected patients with solitary bone metastasis. Additionally, while checkpoint inhibitors have shown limited efficacy in treating uveal melanoma, there is currently no role for BRAF inhibitors in this type of cancer due to the absence of BRAF mutations. MEK inhibitors have also not shown a significant benefit in terms of survival as compared to other treatment options such as Dacarbazine [14].
Additionally, anti-PD1 checkpoint inhibitors have shown a low efficacy of about 9% in treating uveal melanoma [15].
It is important to maintain a high suspicion index for the possibility of metastatic disease in patients with a previous history of malignant melanoma, and they should seek early consultation if they experience any pain and swelling that does not go away. A multidisciplinary approach is necessary, especially for surgical oncology, particularly in unusual places or situations. Radiotherapy remains the treatment of choice, but radical resection may be considered in selected patients with solitary bone metastasis to achieve long-term survival. Bone scans and plain radiographs are useful for detecting bone metastases, which are typically osteolytic or mixed osteolytic-osteoblast. Although limited studies have shown some benefit of immune checkpoint inhibitor treatment in patients with extra hepatic late-occurring metastasis, metastatic uveal melanoma is generally resistant to immune checkpoint inhibition due to its low immunogenicity and mutational burden [14-16].
For 15-month follow-up, the patient showed no signs of recurrence.
Yes, early detection and a multidisciplinary approach are key in the management of patients with bone metastases from malignant melanoma. The involvement of specialists from different fields such as radiology, pathology, medical oncology, radiation oncology, and surgical oncology can lead to a better outcome for the patient.
Additionally, close follow-up is recommended for patients who have had a previous history of malignant melanoma to monitor for any potential recurrence or development of metastases. This can include regular physical examinations, imaging studies, and blood tests to assess for tumor markers. Treatment options for metastatic disease should be individualized based on the patient’s overall health status, extent of disease, and response to prior therapies. A multidisciplinary team consisting of oncologists, radiologists, and surgeons can work together to develop a comprehensive treatment plan that provides the best possible outcomes for the patient.
It is important to note that treatment options should always be individualized and based on a patient’s specific case, including the extent and location of their bone metastasis, overall health, and other factors. Therefore, a multidisciplinary team approach with experts in oncology, surgery, and radiation therapy should be involved in developing the best treatment plan for each patient. Additionally, clinical trials investigating new treatment options should also be considered as they may offer promising results for patients with uveal melanoma and bone metastases.
All authors contributed equally in writing to this manuscript.
The authors declare that they have no known financial or interpersonal conflicts that could affect the research presented in this study.
None.
Copyright: © 2024 Luljeta Abdullahu and Armend Jashari. This is an open-access article distributed under the terms of the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original author and source are credited.









 Open Access by
Acta Scientific is licensed under a Creative Commons Attribution 4.0 International License
Based on a work at https://actascientific.com
ff